







Online mumfluencers are dropping heavy hints about ‘medically supported weight loss’ – but doctors warn some adverts are ‘irresponsible’
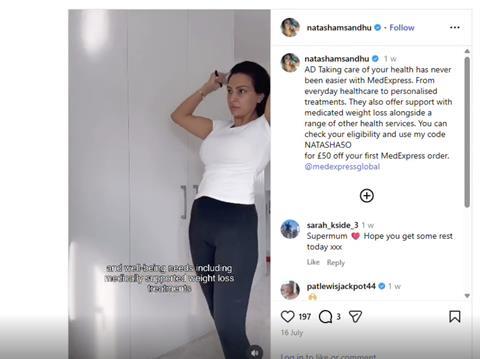
Holding her baby on one hip, Natasha Sandhu tells her half a million Instagram followers: “Between looking after the kids, home, dog and being a good partner, I always forget to look after me.”
Cutaways show the influencer making the bed, getting on a Peloton bike, applying lipstick and yawning as she feeds her baby milk from a bottle. “If that sounds like you, that’s where MedExpress comes in. They offer access to a range of treatments, including medically supported weight-loss treatments,” she adds in a post earlier this month, before offering followers a personalised code for £50 off their first MedExpress order.
A post by another influencer, Jodie Malins, offers the same discount with another personalised code. “MedExpress offers a discreet, clinically guided way to access a range of treatments for health and wellbeing needs, including medicated weight-loss treatments, all found online,” she says.
If those scripts sound cryptic, that could be deliberate. Welcome to the grey area of talking to people about prescription medicines without actually talking about them. It’s a modern-day Rorschach test: one scroller sees a health service; another, already clued up about GLP-1s, sees Mounjaro without it ever being named.
Advertising prescription-only medicines (POMs) like Mounjaro and WeGovy to the public is against the law. Companies can advertise consultations and weight-management services, but not the drugs themselves.
Yet GLP-1s are exactly how MedExpress makes most of its money. Parent company HeliosX saw sales grow from £178m to £777m last year across the UK, US, Germany and Canada. Its growth was “primarily driven by an increase in sales of GLP-1 weight-loss products in the UK”, according to its latest accounts.
Blurred lines
Alongside such growth and intense public interest, MedExpress and others have already had previous rulings against them. In December, the ASA upheld a complaint against MedExpress for a paid-for Instagram ad featuring a video of a woman taking full-length selfies in a mirror with overlaid text stating: “I wish I knew sooner that I could lose post-baby weight with a medicated weight-loss treatment from MedExpress”. It said the advert was “irresponsible” and “included a harmful gender stereotype”. It also consulted with the Medicines & Healthcare products Regulatory Agency (MHRA) to conclude that although the advert did not include a named POM, it breached the advertising code by providing a direct link to a page that featured Mounjaro and Wegovy.

“Marketing aimed at new mothers should prioritise balanced health messaging”
The ASA says it’s now more alive to what it calls “indirect promotion”. In recent guidance, it has reiterated that it looks at the whole customer journey, from watching the advert to clicking through to a landing page, when assessing whether a promotion is likely to lead consumers towards a prescription-only medicine.
MedExpress has been paying attention, and the latest adverts and posts are quite different. Its own guidance to influencers is extremely close to the ASA’s latest clarifications: do talk about the weight-loss service. Don’t use the word “prescription”. Do show the MedExpress shipper box. Don’t show one specific product.
On an easily accessible page on its website, MedExpress invites ‘affiliates’ to “get started” by sharing their social media handle. They then get a code that offers £40 off to their followers, and they earn £40 for every “successful referral”.
Sandhu and Malins’ posts didn’t link to MedExpress. The online pharmacy was tagged in the post, but visitors had to make their own way to the website to redeem the discount code. From its landing page, however, it takes one click to reach the weight-loss page, which displays a carousel comprised exclusively of POMs.
What are the rules for weight-loss marketing?
The rule sounds simple: prescription-only medicines cannot be advertised to the public. That ban is reflected in the MHRA Blue Guide and the CAP Code, and it applies whether a product is named outright or promoted by implication.
In the fast-growing market for GLP-1s, however, the boundary can be blurred. The ASA’s own research suggests public understanding is patchy. In a survey of 2,000 people, fewer than half knew GLP-1s were prescription-only medicines and more than a third were unaware there were restrictions on advertising them. Some 65% thought weight-loss service ads could put pressure on people to lose weight.
The ASA analysed 95,000-plus unique paid online ads from 44 advertisers – including 35,000 relating to weight-management services – between February 2025 and January 2026. About 900 ads from 38 advertisers were assessed as likely to breach the rules, with concerns including named medicines, wording that implied prescription-only medicines and images of branded injection pens.
Enforcement has had an effect. When monitoring began in February 2025, 7% of ads were considered likely to breach the rules. After targeted enforcement notices, that fell to 1%.
But the regulator warns that avoiding the name of a medicine does not make an ad compliant.
Businesses can advertise legitimate weight management services, consultations and clinical support, but the focus must remain on the service, assessment, professional oversight, patient suitability and broader healthcare support – not on access to a specific drug.
A compliant ad should not drive consumers to a non-compliant destination, and links should not feature named prescription-only medicines.
Doctors and nutrition experts are sounding the alarm, concerned about the big picture and subliminal messaging to a vulnerable group, regardless of whether the right concoction of words has been adhered to.
“The first year after birth demands extreme caution,” says Dr Federica Amati, Zoe’s head nutritionist and author of The Appetite Reset: How to Eat, Drink and Thrive Before, During and After GLP-1s. “We should challenge the pressure on new mothers to ‘bounce back’. Bringing a child into the world is a profound physiological event, and rushing into pharmaceutical weight loss at the expense of recovery is unfair and potentially harmful. ”
Dr Nadia Ahmad, director of The Weight Care Clinic, agrees that “as both a doctor and a mother who gave birth last year, I think we need to be very cautious. The postnatal period is a particularly vulnerable time, with many women experiencing hormonal changes and significant pressure around body image. Any marketing aimed at this group should prioritise balanced health messaging over rapid weight loss and should never downplay the fact that these are prescription medicines requiring an individual medical assessment.”
Ahmad’s own clinic looks at nutrition, lifestyle, mental wellbeing and medical history. “Medication is just one part of that conversation, not the headline,” she says. “We’ve deliberately focused on doctor-led, evidence-based care. We place a strong emphasis on ongoing support alongside prescribing, as sustainable weight management is about much more than medication alone.
“Many women enter the postpartum period already depleted from pregnancy and childbirth. Iron deficiency, vitamin D deficiency and low calcium intake are all relatively common and can contribute to fatigue, poor recovery and reduced overall wellbeing.”
GLP-1s work by reducing appetite, which can make it hard to meet postpartum nutritional needs, she says.
Richa Puri, an independent clinical pharmacist specialising in women’s hormonal health, breaks those risks down. “From around three months, many new mothers frequently start running on too little fuel. They tend to eat less just at the time their bodies still need plenty of energy to properly recover. By four to eight months, we typically see the widest nutritional gaps. Iron stores can be at their lowest, protein intake is often inadequate for muscle repair, and intakes of vitamin D, calcium and B vitamins are frequently suboptimal.
“Even at nine to 12 months, many women are still not nutritionally replete, particularly if they’ve breastfed. The issue with GLP-1s is they reduce appetite at a time when nutritional needs are still elevated. We’re seeing data showing micronutrient deficiencies and lean mass loss emerging within six to 12 months of use. In a postpartum context, that risks compounding existing gaps rather than correcting them.”

“We should challenge the pressure on new mothers to ‘bounce back’”
The legal position
After being contacted by The Grocer, a MedExpress spokeswoman said the company had asked Malins and Sandhu to remove the posts “as a precautionary measure” to “make sure we stay aligned to our internal advertising guidelines”. Neither influencer responded to a request for comment.
The spokeswoman said: “Patient safety is always our priority, and we take our responsibilities under applicable legislation, regulation and advertising standards seriously, including where third parties are involved. Our approach is to ensure that access to healthcare is accompanied by appropriate clinical assessment, information and support so that decisions about treatment are made safely and appropriately for each individual.”
The ASA has made no findings on the posts, nor has it previously ruled against affiliate adverts referencing discount codes that do not contain explicit or implied references to POMs.
“They are primarily focused at the moment on companies that advertise the prescription over the consultation – that’s the most obvious breach of the ban,” says Katrina Anderson, partner and head of advertising at Mills & Reeve. “As advertising has moved online, they’re much more active in using AI scraping to monitor adverts and have to direct it towards certain things. But it doesn’t mean they wouldn’t investigate complaints.”
The law, however, affords greater protection to vulnerable consumers, so theoretically any complaint made to the ASA would be assessed through a rigorous social responsibility lens. “In general, consumers are protected under the law from being misled, aggressive commercial practices, etc. The law recognises that certain consumers are particularly vulnerable and affords them greater protection. I’d expect that any court or regulator would conclude it’s reasonably foreseeable that new mothers may be particularly vulnerable in relation to ads for weight-loss medication and would therefore find that this higher standard applies.”
MedExpress’ own adverts are prolific. At the time of writing, it had 180 adverts mentioning weight loss live across Meta platforms Facebook, Instagram, Messenger and Threads [Meta Ad Library]. Some highlight price drops, others “weight-loss treatment in a once-daily pill”, which leads to information about the prescription-only Wegovy pill.
The sheer quantity is only part of the story. The adverts also show MedExpress pushing another boundary: who might be encouraged to see themselves as eligible.
Some 39 of them flag that people with a BMI of 25+ “might be eligible for weight management treatment”, a lower threshold that MedExpress first advertised in March. Such prescribing is known as “off-label”, meaning it differs from the medicine’s official licence.
Wegovy and Mounjaro were approved by the MHRA to treat type 2 diabetes and weight management for adults with a BMI of 30 or more (obesity) as well as those with a BMI of 27-30 (overweight) who also have a weight-related health problem such as prediabetes or high blood pressure.
On its website, MedExpress reassures potential patients that “off-label prescriptions are safe, legal and commonly practised”. That leaves patients only just above the “healthy weight” threshold potentially able to access what was until recently an obesity drug.
When The Grocer entered a fictional weight and height to give a BMI of 25 and no medical conditions, we were told Mounjaro’s lowest 2.5mg dose could be suitable, though confirming an order would be subject to an online consultation.
A MedExpress spokeswoman says: “For people with a BMI of 25 or above the options available will depend on their individual circumstances and, where medicines are involved, an appropriate assessment by a prescriber or pharmacist. Over time, we have broadened the range of patients who may be considered for treatment where there is a clinically appropriate reason to do so, with decisions made by a prescriber based on each individual patient’s circumstances.
“Our priority is to ensure that any weight-management treatment offered through MedExpress is clinically appropriate.”
But eating disorder charity Beat is concerned that it has all become too easy. Research manager Umairah Malik says: “We’re concerned that these drugs, particularly in pill form, are being marketed as no more dangerous than taking vitamin tablets when this is not the case. Deciding to start taking weight-loss medication is a decision which must never be taken lightly, and they should only be prescribed following thorough mental health checks, along with ideally in-person physical health checks, and always carried out by a trained healthcare professional. We’d also urge companies to use responsible language during any and all advertising, and not trivialise the serious side effects these drugs could cause.”
Which brings us back to what those new mums scrolling on their phones are likely to think of. The adverts might talk about eligibility and health, but that Rorschach effect matters. Research from the ASA found people with greater knowledge of weight-loss injections were more likely to interpret adverts as promoting them.
“The key question we ask is simple: will the ad likely lead to a consumer requesting a POM? If the answer is yes, it is likely to breach the rules,” Andrew Bishop, ASA investigations executive, explained in a July webinar. “The safest approach remains: advertise a consultation and the healthcare service, not the medicine itself.”
What is and isn’t compliant will only get clearer as the ASA publishes more decisions, setting more precedents around real-life examples in the blurred area.
“Advertisers and regulators are still finding the line on how to advertise a consultation for a disruptive product which itself cannot be advertised. In 18 months’ time we’ll have a larger body of rulings to be able to definitively cover more scenarios,” Anderson predicts.
But for people already primed to read between the lines, the message may be clear long before then.












No comments yet